Upper Back Pain Causes: Muscles, Posture, Ribs, or Something Else?
Understand upper back pain causes, common movement patterns, and warning signs that should not be ignored.
Read article
Athletes do not need rehabilitation that ends when ordinary daily movement becomes comfortable. Cricket, football, running, badminton, martial arts, racquet sports, gym training and competitive events place higher demands on strength, speed, power, balance, coordination and confidence. An athlete may feel almost normal during walking yet remain unprepared for sprinting, cutting, jumping, landing, throwing, kicking, grappling or repeated high-intensity effort.

WHPT Pakistan assesses symptoms, movement, strength, medical context and the activities the patient needs to regain before selecting treatment and rehabilitation.
| Feature | Details |
|---|---|
| Audience | Recreational, developing, competitive and masters athletes |
| Available at | WHPT Pakistan, Bahria Town, Lahore |
| Common sports | Cricket, football, running, badminton, gym training and martial arts |
| Main focus | Injury recovery, athletic capacity and return to performance |
| Assessment | Diagnosis, strength, movement, workload and sport demands |
| Progression | Rehabilitation to controlled drills, training and competition |
| Primary goal | Return the athlete through measurable criteria rather than pain relief alone |
Physical therapy for athletes progresses beyond ordinary daily function. WHPT assesses the injury, sport demands, training load and current capacity, then rebuilds mobility, strength, power, conditioning and confidence through criteria-based return to training and competition.
Urgent assessment is required after major trauma, obvious deformity, suspected fracture or dislocation, inability to bear weight, loss of consciousness, repeated vomiting after a head injury, chest pain, severe breathlessness, a cold or pulseless limb, rapidly increasing swelling, fever with a hot joint, new bladder or bowel dysfunction, saddle numbness or rapidly progressive weakness. Athletes with suspected concussion, cardiac symptoms, heat illness or serious neurological change should not be encouraged to “push through” training.
Pain relief is not the same as athletic readiness. A runner may need repeated single-leg loading; a cricketer may need sprinting, throwing or bowling tolerance; a martial artist may need kicking, pivoting and reactive balance; and a strength athlete may need confidence under progressively heavier loads. WHPT identifies the physical qualities required by the sport and measures whether they have actually returned.Athletic readiness is also affected by fatigue. A player may perform a single hop or sprint well when fresh but lose control after repeated efforts. For this reason, later-stage rehabilitation may include repeated tests, change-of-direction work and drills completed after controlled conditioning. The aim is not to exhaust the athlete for display; it is to understand whether quality is maintained when the sport becomes demanding.
We also look beyond the injured body part. Training spikes, inadequate recovery, previous injuries, poor movement options, reduced strength and fear of reinjury may all influence performance. Rehabilitation therefore combines local tissue recovery with whole-body conditioning and a realistic plan for returning to practice, competition and long-term training.The rehabilitation plan should also fit the competitive calendar. A tournament, trial or season deadline may influence priorities, but it cannot change biological healing. WHPT discusses what can be modified, which qualities can be trained safely and what risks remain. Shared decision-making is more responsible than promising a fixed date simply because the athlete or team needs one.
WHPT Clinical Principle Treat the injury. Train the required capacity. Return the athlete through criteria—not pressure or the calendar alone.
An athlete-focused physiotherapy assessment may be useful when pain, injury, surgery or loss of capacity is limiting training or competition. Common reasons athletes contact WHPT include:
Urgent assessment is required after major trauma, obvious deformity, suspected fracture or dislocation, inability to bear weight, loss of consciousness, repeated vomiting after a head injury, chest pain, severe breathlessness, a cold or pulseless limb, rapidly increasing swelling, fever with a hot joint, new bladder or bowel dysfunction, saddle numbness or rapidly progressive weakness. Athletes with suspected concussion, cardiac symptoms, heat illness or serious neurological change should not be encouraged to “push through” training.
Physical therapy for athletes is rehabilitation designed around the physical demands of sport. It addresses injury, surgery, pain, movement limitation and loss of performance capacity while helping the athlete progress safely from basic function to training and competition. The process may involve the injured tissue, the whole kinetic chain, conditioning, load management and psychological readiness.
The term athletic physical therapy does not mean every patient performs advanced drills immediately. Early rehabilitation may focus on swelling, mobility, protected loading and muscle activation. Higher-level work is introduced only when healing, symptoms and objective tests support progression. The program should match the athlete’s sport, position, age, competition level and training environment.
The Athletes page explains how WHPT helps a defined audience across injury, surgery and return to performance. Sports Physiotherapy remains the detailed service page explaining the specialist approach, while Sports Injuries introduces common injury categories. Diagnosis pages retain ownership of condition-specific keywords and protocols. This separation creates a clear pathway without repeating the same content across multiple URLs.Preseason or movement screening may identify measurable limitations, but no screen can predict every injury. WHPT uses screening to guide training decisions, establish baselines and identify symptoms that need assessment. It is not marketed as a guarantee that an athlete will remain injury-free.
Common barriers that delay athletic recovery include:
Athletic recovery time depends on the diagnosis, tissue healing, surgery, severity, previous injury, sport demands and the athlete’s training status. A mild muscle injury may recover over weeks, while ACL reconstruction, major tendon repair, fracture or complex shoulder surgery may require many months. Return to basic exercise is usually earlier than unrestricted competition. Progress should be judged through symptoms, strength, movement quality, conditioning, sport-specific exposure and confidence rather than a date alone.Youth athletes require additional attention to growth, school load and sport specialization. Pain around a growth plate, repeated stress injury or a sudden loss of performance should not be dismissed as ordinary training soreness. Masters athletes may have excellent fitness but need greater consideration of tendon recovery, arthritis, previous surgery and overall medical health. Neither age group should be placed into a one-size-fits-all timeline.
The assessment may include:
The assessment connects the medical diagnosis with the athlete’s real performance demands. The therapist identifies the injured structure, current healing stage, contributing factors and the minimum capacities required for safe return.
Injury History, Training Load and Medical Screening
The history reviews mechanism, symptom behavior, previous injury, surgery, medication, imaging, competition schedule, weekly training, recent load changes, sleep and recovery. Red flags, concussion symptoms and medical restrictions are screened before physical testing. The therapist asks whether the athlete continued playing, whether swelling developed immediately and whether the symptoms change between warm-up, competition and the following day. These details help distinguish a recent tissue injury from overload, referred pain or a problem that needs imaging or medical review.
Movement, Strength and Capacity Testing
Testing may include joint range, strength, balance, hopping, landing, running tolerance, throwing or lifting tasks. The therapist selects measures according to injury stage. Early testing protects healing tissue; later testing challenges the qualities required by sport. Testing is repeated only when it will influence a decision. Examples may include calf-raise endurance after ankle injury, quadriceps strength after knee surgery, shoulder strength for overhead athletes or repeated hopping for field-sport return. Numbers are interpreted alongside movement quality and the athlete’s symptoms.
Sport, Position and Performance-Demand Analysis
A wicketkeeper, fast bowler, footballer, runner, martial artist and powerlifter do not need the same program. The therapist maps acceleration, deceleration, jumping, change of direction, contact, overhead activity, endurance and technical demands relevant to the athlete. Training age also matters. A developing athlete may need basic movement, strength and recovery education before advanced drills. An experienced competitor may require more specific speed, power and workload exposure. Rehabilitation should meet the athlete at the current level rather than imitate elite-sport exercises seen online.
Rehabilitation Planning and Return-to-Sport Criteria
Goals are converted into milestones for mobility, strength, power, workload and sport participation. The athlete progresses from individual rehabilitation to controlled drills, modified practice, full training and competition as appropriate. Reassessment determines whether each step is tolerated.
A successful return requires coordination between tissue healing, physical preparation and the training environment. Rehabilitation should communicate with the surgeon, physician, coach or strength professional when relevant and with the athlete’s consent.
Athlete care may include coordination with:
Communication should be practical and consent-based. The therapist does not replace the coach, and the coach does not replace clinical assessment. The best return plan aligns medical safety, rehabilitation criteria and sport exposure so the athlete is neither protected indefinitely nor rushed into a level the body cannot tolerate.When communication with a coach is appropriate, the information should be functional: which activities are allowed, what volume is tolerated, which signs require stopping and when reassessment will occur. Detailed medical information remains private unless the athlete authorizes its release.
WHPT adapts rehabilitation to the athlete’s sport and injury rather than offering one universal athletic program.
| Athlete or sport demand | Main rehabilitation focus | Relevant WHPT destination |
|---|---|---|
| Running and field sport | Load, strength, running, hopping and change of direction | Sports Physiotherapy / Lower Limb pages |
| Cricket and overhead sport | Shoulder, elbow, throwing, sprinting and workload | Sports Injuries / Upper Limb pages |
| Martial arts | Kicking, pivoting, balance, impact and conditioning | Sports Physiotherapy / Alpha transition |
| Gym and strength sport | Technique, graded loading and confidence under resistance | Therapeutic Exercise / Sports Physiotherapy |
| After ACL or meniscus injury | Strength, hopping, running and return-to-sport criteria | ACL / Meniscus pages |
| After ankle sprain | Mobility, calf strength, balance and cutting | Ankle Sprain page |
| After shoulder injury | Range, cuff strength, power and overhead tolerance | Rotator Cuff / Shoulder pages |
| After surgery | Healing-aware progression and surgeon coordination | Post-Surgical Rehabilitation |
The sport label alone does not determine treatment. Two runners with knee pain may have different diagnoses, training histories and capacity deficits. Similarly, the same ACL procedure creates different return demands for a recreational gym-goer and a competitive footballer. Assessment defines the pathway.In-season rehabilitation may differ from off-season rehabilitation. During the season, the aim may be to preserve participation while controlling load and maintaining key qualities. Off-season care may allow a larger rebuilding phase. The choice depends on diagnosis, risk, competition importance and the athlete’s long-term development—not on a blanket rule to rest or continue.
Physiotherapy should not delay urgent management of fracture, dislocation, severe concussion, neurovascular injury, infection, cardiac symptoms or significant neurological change. Some tendon ruptures, unstable ligament injuries and traumatic joint injuries require early orthopedic review before exercise progression.
The assessment may include:
Planning starts with the end demand. The therapist works backward from the sport, position and competition level to identify the mobility, strength, power, conditioning and skill exposure required. The athlete then progresses through stages that protect tissue while reducing unnecessary deconditioning.Return-to-sport planning usually involves several decisions rather than one clearance. Return to participation may mean controlled individual drills. Return to sport may mean full team training. Return to performance means tolerating the volume, intensity and confidence required to compete effectively. WHPT communicates which stage the athlete has reached so partial progress is not mistaken for complete readiness.
The assessment and return plan may include:
Injury mechanism, diagnosis, surgery details and tissue-healing stage
Training volume, intensity, recent spikes, surfaces, footwear and recovery pattern
Joint range, strength, endurance and side-to-side comparison where relevant
Balance, landing, hopping, running, throwing, kicking or lifting tests
Sport- and position-specific movement analysis
Confidence, fear of reinjury and readiness for controlled exposure
Practice progression from individual drills to modified and full training
The process moves from diagnosis and symptom control toward progressive sport preparation. The exact sequence changes with the injury and stage.
Step 1: Diagnosis and Baseline Testing
The therapist reviews the injury, medical information and sport demands, then establishes a baseline for movement, strength and function. Urgent or surgical concerns are referred.
Step 2: Protect Healing and Restore Basic Function
Pain, swelling, mobility, walking or basic movement are addressed while safe muscle activation and conditioning are maintained.
Step 3: Rebuild Strength and Tissue Capacity
Exercise intensity and volume increase gradually. The program targets the injured region and the wider kinetic chain needed for sport.
Step 4: Develop Power, Agility and Sport Skills
Running, jumping, landing, cutting, throwing, kicking, contact preparation or heavy lifting are introduced according to the sport.
Step 5: Return to Training and Competition
The athlete moves through modified practice, full training and competition while workload and next-day response are monitored.
| Stage | What happens | Why it matters |
|---|---|---|
| Diagnosis and baseline | Injury, sport demands and current function are assessed | Defines a safe starting point |
| Restore basic capacity | Pain, swelling, movement and early strength are addressed | Prepares the athlete for loading |
| Develop athletic qualities | Strength, power, balance and conditioning progress | Matches sport demands |
| Sport exposure | Running, agility, throwing, kicking or lifting drills are added | Bridges clinic and practice |
| Return and maintenance | Full training response and long-term program are reviewed | Reduces premature discharge |
Your Role as an Athlete in Rehabilitation
Athletes need to report symptoms honestly, follow temporary restrictions, complete the agreed home and gym work, protect sleep and recovery, and avoid adding unplanned high-intensity sessions. Rehabilitation is a training process: consistency usually matters more than occasional heroic effort. Tell the therapist about competition deadlines, team pressure and fear of reinjury so the plan can address them directly. The athlete should also keep a simple record of training exposure when requested. Session duration, running distance, drill intensity, pain during activity and next-day response can reveal patterns that memory alone misses. This information helps progress the program without reacting to one isolated good or bad day.
When the diagnosis and progression are appropriate, athlete-focused rehabilitation may help:
| Potential benefit | What it may allow |
|---|---|
| Reduced pain and swelling | More comfortable movement and early training |
| Restored strength and power | Better tolerance of sport-specific force |
| Improved balance and control | Safer landing, cutting and contact preparation |
| Objective return criteria | Clearer decisions about practice and competition |
| Training-load education | More sustainable progression after return |
Results vary according to diagnosis, severity, adherence, healing and sport demands. Physical therapy cannot guarantee a specific competition date or eliminate all future injury risk. It can provide a structured, measurable process that prepares the athlete more completely than pain-based return alone.A good outcome is not always a return to the identical previous program. Some athletes return with a modified technique, workload, position or competition schedule. These changes are not automatically failure; they may represent a sustainable way to continue sport while respecting tissue and health factors.

Some muscular effort, fatigue and mild short-lived discomfort can occur during progressive loading. The acceptable response depends on the tissue, injury stage and exercise goal. Sharp pain, instability, major swelling, neurological symptoms or a significant next-day loss of function are not ignored as evidence of a “good session.”
Athletes often tolerate high effort, which can make them underreport symptoms. The therapist monitors technique, speed, range, swelling and next-day response rather than relying on toughness. The program can still be demanding while remaining clinically controlled.
Athlete rehabilitation is generally safe when the diagnosis, healing restrictions and exercise dosage are appropriate. Safety requires screening for fracture, concussion, cardiac symptoms, neurovascular compromise and surgical precautions before high-load testing.
The highest-level drill is not automatically the best drill. Progressions should have a clear purpose and an entry criterion. WHPT explains why a task is included, what response is expected and what signs mean the load should be changed.
Training Responses and Warning Signs During Athlete Rehabilitation
| Response or sign | Possible meaning | Next step |
|---|---|---|
| Mild muscle effort or short-lived soreness | Expected training response | Continue planned dose |
| Persistent swelling or major next-day loss of function | Load may be excessive | Reduce and reassess |
| Joint giving way, locking or sharp instability | Possible structural problem | Prompt clinical review |
| Headache, confusion or repeated vomiting after impact | Possible concussion | Stop sport and seek medical assessment |
| Chest pain, collapse or severe breathlessness | Emergency concern | Seek urgent care |
Athletes Who Need Additional Precautions or Coordination
Additional planning may be needed for youth athletes, masters athletes, pregnancy, diabetes, asthma, heart conditions, previous concussion, repeated stress injury, osteoporosis, recent surgery, use of anticoagulants or a history of significant instability. The athlete should disclose medications, supplements and relevant health conditions. Medical clearance may be necessary before vigorous testing or return to contact sport. Athletes using pain medication to complete training should tell the clinician because symptom suppression can complicate load decisions. Repeated use of injections, rapid weight loss, dehydration or training through illness also requires honest discussion and, when indicated, medical review.
Aftercare and Training Guidance for Athletes
The Athletes page is audience-focused. It answers who WHPT helps, what athletes can expect and how rehabilitation progresses from injury to performance. It links recreational and competitive athletes to the correct service and diagnosis pages.
| Feature | Athlete audience page | Sports Physiotherapy / diagnosis pages |
|---|---|---|
| Primary role | Who WHPT helps and the athlete journey | Detailed service and condition guidance |
| Main topics | Sport demands, recovery stages and return to performance | Service methods, injuries, symptoms and protocols |
| Keyword ownership | physical therapy for athletes; athletic physical therapy | sports physiotherapy and diagnosis-specific terms |
| Internal-link role | Routes athletes to the correct service and condition | Provides depth and links back to the athlete pathway |
| Cannibalization control | Brief diagnosis summaries only | Owns detailed injury, treatment and recovery content |
Sports Physiotherapy is the specialist service page and should own detailed service-method, sports-physio and clinical-delivery keywords. Sports Injuries and diagnosis pages explain specific conditions. The pages support each other through internal links instead of competing for identical terms.
External authority resource: American Academy of Sports Physical Therapy — Educational Resources

Symptoms can improve before muscle force, tendon capacity, reactive balance or conditioning returns. An athlete may pass daily-life tasks but fail repeated sprints, late-session cutting or high-velocity kicking. Returning at that stage can expose the remaining deficit under pressure.
WHPT therefore progresses the athlete through increasing speed, load, complexity and fatigue. Success is judged by meaningful sport capacity and sustainable training—not by how comfortable the athlete feels while resting.The final phase also prepares the athlete for decision-making outside the clinic. They should understand how to increase weekly load, recognize early warning signs and maintain the strength qualities most relevant to the injury. Long-term self-management is part of return to performance.
Athletes need clinical reasoning, progressive loading and a clear return pathway. WHPT combines physiotherapy assessment with access to condition-specific rehabilitation and, when appropriate, a supervised transition to strength, conditioning and martial arts environments through Alpha Fitness & Martial Arts Club.
| WHPT Pakistan approach | Why it matters |
|---|---|
| Diagnosis before performance drills | Protects the athlete from training an unknown injury |
| Sport and position analysis | Makes rehabilitation relevant to real demands |
| Progressive loading | Restores tissue and whole-body capacity |
| Objective testing | Identifies deficits hidden by pain relief |
| Training-load planning | Reduces sudden return spikes |
| Condition-specific pathways | Adds depth for ACL, shoulder, ankle and other injuries |
| Alpha performance transition | Bridges rehabilitation and long-term training |
It is rehabilitation designed around the physical demands of sport, from injury assessment and tissue recovery to strength, conditioning, sport-specific drills and return-to-sport testing.
No. Recreational, school, university, masters and competitive athletes can all benefit. The program is matched to the person’s actual sport and goals.
Timing depends on diagnosis and healing. Return should also consider strength, movement quality, sport exposure, confidence and response to full training—not time alone.
Often some training can continue with modification. The therapist identifies what can be maintained safely without repeatedly aggravating the injury.
Not always. Imaging is useful when the examination raises a specific question or medical decision. Many sports problems can begin with clinical assessment.
Testing may examine strength, balance, hopping, running, landing, agility, throwing, lifting or other sport-specific tasks. The test battery depends on the injury and sport.
No program prevents every injury. Strength, workload management, movement preparation and recovery strategies may reduce modifiable risks and improve readiness.
WHPT can assess athletes from different sports and adapt rehabilitation to running, cricket, martial arts, gym and field-sport demands.
Suitable athletes may transition to progressive strength, conditioning, flexibility or martial arts training through Alpha Fitness & Martial Arts Club.
WHPT Pakistan provides athlete-focused physiotherapy and return-to-sport rehabilitation in Bahria Town, Lahore.
Discharge from pain-focused treatment may not mean the athlete is ready for full performance training. Many athletes need a bridge that develops greater strength, work capacity, speed, mobility and confidence under sport-like fatigue. The bridge may include higher-volume strength work, repeated sprint conditioning, loaded carries, jumping or sport-specific practice that is no longer medical treatment but still benefits from a planned handover.
Where appropriate, WHPT may coordinate a transition to Alpha Fitness & Martial Arts Club for strength and conditioning, flexibility, personal training or martial arts. The transition begins only when the clinical problem is stable and the athlete can tolerate the next stage safely.
An athlete returns when walking and light jogging feel comfortable, but testing still shows reduced single-leg strength, power and confidence. Sport exposure reveals the deficit only when speed and fatigue increase. A staged return plan rebuilds these qualities before unrestricted competition.
Return to sport should follow measured capacity, graded exposure and the athlete’s real performance demands.
Whether the goal is returning to cricket, football, running, badminton, gym training, martial arts or another sport, an assessment can identify the diagnosis, current capacity and safest route back to training.
WHPT Resources

Understand upper back pain causes, common movement patterns, and warning signs that should not be ignored.
Read article →
Explore common causes of lower back pain, what symptoms may reveal, and when an assessment can help.
Read article →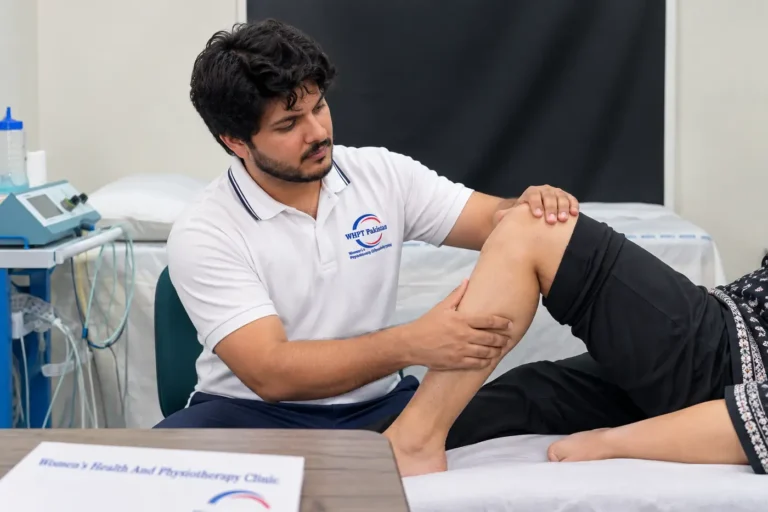
A knee assessment looks beyond pain alone. Learn how movement, strength, function, history, and symptoms guide rehabilitation.
Read article →
Some exercises may temporarily aggravate an irritated knee. Learn how to modify loading without giving up movement completely.
Read article →
Knee pain can return even after symptoms improve. Learn why recurrence happens and which factors may need more attention.
Read article →
Heat and ice can both help knee symptoms in certain situations. Learn when each option may be useful and what…
Read article →EXCELLENT Based on 19 reviews
 Posted on Google

 MUHAMMAD USMAN SALEEM MUHAMMAD SALEEMIt’s actually the place where Doctors have a right knowledge to treat. Strongly recommend best clinic in LahorePosted on Google
 Nasira ShaheenVery satisfied with the services and care given to my daughter from Dr. Rabail. She wasn't able to speak sentences and many words before and has improved more then that now in her behavior and speech. I am very grateful for Dr. Rabail and WHPT and had no concerns through our sessions with them.Posted on Google
 Mahnoor MughalMy father-in-law experienced severe low back spasms, and WHPT Pakistan's at-home physiotherapy service was a lifesaver. The therapist arrived fully equipped and provided highly effective, personalized care right in the comfort of our home. The treatment not only eased his pain but also gave him exercises to help prevent future episodes. The convenience and quality of care were superb, and we’re very grateful for their compassionate and professional service!Posted on Google
 Noaman Younasgood doctor team coprative doctorPosted on Google
 Ali AghadeerStaff is very professional and humble Great experiencePosted on Google
 Fatima ZahraI was tired of writing “physiotherapy near me” for my neck pain. Luckily, i ended up in WHPT Pakistan, arguably the most trusted physiotherapy clinic in Bahria Town Lahore. Highly recommendedVerified by TrustindexTrustindex verified badge is the Universal Symbol of Trust. Only the greatest companies can get the verified badge who has a review score above 4.5, based on customer reviews over the past 12 months. Read more
WHPT Pakistan
1st Floor, Plaza 82, Block AA Commercial,
Bahria Town, Lahore