Upper Back Pain Causes: Muscles, Posture, Ribs, or Something Else?
Understand upper back pain causes, common movement patterns, and warning signs that should not be ignored.
Read article
People searching for a chiropractor in Lahore are often looking for relief from back pain, neck stiffness, restricted spinal movement, sciatica, headaches, or the feeling that a joint needs to be “adjusted.” At WHPT Pakistan, these concerns are managed through physiotherapy-led spinal assessment, manual therapy, and active rehabilitation.

WHPT assesses spinal pain, movement, neurological findings and relevant risks before selecting manual therapy, exercise or referral. Treatment is based on the person’s presentation rather than a promise to realign the spine.
| Feature | Details |
|---|---|
| Service | Physiotherapy-led spinal manipulation, joint mobilization, and manual therapy where indicated |
| Location | WHPT Pakistan, Bahria Town, Lahore |
| Provider | Physiotherapists with relevant manual therapy training; WHPT is not represented as a chiropractic clinic |
| Common reasons for consultation | Back pain, neck pain, stiffness, restricted movement, selected headaches, thoracic pain, and some musculoskeletal conditions |
| Assessment | Medical history, neurological screen, movement, strength, joint mobility, red flags, and patient goals |
| Treatment options | Manipulation, mobilization, soft-tissue treatment, exercise, education, and movement retraining |
| Primary goal | Reduce pain or stiffness enough to improve movement and progress active rehabilitation |
| Key limitation | An adjustment does not realign the entire spine, cure every condition, or replace exercise and medical care |
A spinal adjustment is a manual therapy technique in which a trained clinician applies a controlled movement to a spinal or peripheral joint. A high-velocity, low-amplitude thrust may produce a popping sound, but the sound does not mean that a bone was out of place or has been permanently realigned. Research suggests spinal manipulation may provide modest short-term improvement for selected people with back or neck pain. WHPT uses it only after assessment, informed consent, safety screening, and discussion of alternatives, and combines it with active rehabilitation when appropriate.
These symptoms do not automatically mean that manipulation is needed. Two patients with similar pain may require completely different treatment.

A chiropractor is a healthcare professional trained in chiropractic care, a field that commonly uses spinal manipulation and other conservative approaches for musculoskeletal complaints. In countries where chiropractic is formally regulated, chiropractors complete profession-specific education and may use the title Doctor of Chiropractic. They are not medical doctors unless they hold a separate medical qualification.
Patients often use the words chiropractor, bone setter, spinal adjustment specialist, and physiotherapist interchangeably. These professions and titles are not identical. The important questions are the practitioner’s verified qualification, training, scope of practice, assessment process, safety standards, and whether the proposed treatment matches the patient’s condition.
WHPT clinicians are physiotherapists. We address chiropractor-related search intent transparently because many patients use “chiropractor near me” when they are actually seeking skilled manual therapy, spinal assessment, or relief from back and neck pain.

Spinal adjustment is a common public term for spinal manipulation. The clinician positions a joint and applies a brief, controlled force within a carefully selected direction and range. In manual therapy, this is often described as a high-velocity, low-amplitude, or HVLA, thrust.
Manipulation differs from mobilization. Mobilization uses slower, graded, repeated movements without a rapid thrust. Some patients are better suited to mobilization, exercise, soft-tissue treatment, or education than to manipulation.
The purpose of a spinal adjustment is not to force every joint to crack. A clinically useful manipulation may aim to reduce pain, improve short-term movement, decrease guarding, or create an opportunity for exercise and functional retraining.

The popping sound during an adjustment is usually associated with rapid pressure changes and gas movement within a synovial joint. This process is often called cavitation.
The sound does not prove that a vertebra was “put back,” that a disc was corrected, or that the treatment was successful. An effective manual therapy session may occur without any sound, while several loud pops may produce no meaningful improvement.
WHPT evaluates pain, range of motion, movement quality, muscle function, and the patient’s ability to perform relevant tasks rather than counting how many joints made a sound.
| Technique | How It Is Performed | Possible Clinical Use | Important Limitation |
|---|---|---|---|
| Spinal manipulation / HVLA thrust | A brief, controlled movement delivered at higher speed and low amplitude | Selected pain or mobility presentations after screening | Not appropriate for every patient or every region |
| Joint mobilization | Slower, graded, repeated passive movement | Pain modulation and mobility work with more adjustable force | Still needs active follow-through |
| Soft-tissue techniques | Hands-on pressure or movement applied to muscles and related tissues | Reduce sensitivity or guarding and improve exercise tolerance | Does not permanently lengthen or “release” every tissue |
| Self-mobilization | The patient performs a prescribed movement using body position, a towel, or another safe tool | Builds independence and repeated movement practice | Must be selected for the correct condition |
| Therapeutic exercise | Active mobility, strength, control, endurance, and task practice | Builds long-term capacity and reduces recurrence risk | Requires appropriate progression and adherence |

Spinal manipulation may influence pain perception, joint-related sensory input, muscle guarding, and short-term movement. Its effects are not fully explained by “realignment,” and visible structural change is not required for a patient to feel better.
The practical question is what the treatment allows the patient to do next. A temporary reduction in pain or stiffness may help someone bend, turn, walk, exercise, or return to daily activity more confidently. That window should be used to address strength, mobility, load tolerance, movement habits, sleep, work demands, and other contributors to recurrence.
The response varies. Some patients experience immediate improvement, others notice only a small change, and some do not benefit. Manipulation should not be repeated indefinitely when measurable outcomes do not improve.
Research suggests spinal manipulation can provide modest short-term improvements in pain and function for some people with acute or chronic low back pain. Its effects are generally comparable to other recommended conservative treatments rather than clearly superior to them. Benefits also vary according to patient selection, comparison treatment, technique, and outcome measured.
This evidence supports a balanced role for manual therapy: it can be useful, but it should not dominate rehabilitation or be sold as a correction for every spinal problem.
The National Institute for Health and Care Excellence recommends considering manual therapy, including spinal manipulation, for low back pain with or without sciatica only as part of a treatment package that includes exercise. This directly reflects WHPT Pakistan’s approach: hands-on treatment may help symptoms, but active rehabilitation is what develops lasting capacity.
Read the official NICE guideline on low back pain and sciatica for the full assessment and treatment recommendations.
Manipulation may be considered for selected adults when the examination suggests a mechanical musculoskeletal presentation and no contraindication is present. Possible reasons for considering it include:
These symptoms do not automatically mean that manipulation is needed. Two patients with similar pain may require completely different treatment.

People frequently ask whether they should see a chiropractor for lower back pain. Spinal manipulation may provide modest short-term relief for selected cases of nonspecific low back pain, but the painful area does not reveal the full diagnosis.
Assessment may identify reduced hip movement, poor trunk endurance, sensitivity to bending, lifting demands, prolonged sitting, fear of movement, sleep disruption, or a neurological component. Treatment may include manipulation or mobilization, but also progressive exercise, walking, lifting retraining, education, and a return to normal activity.
Manipulation is not used to “push a slipped disc back into place.” Disc-related symptoms require neurological assessment, monitoring, activity guidance, and medical referral when weakness, numbness, bladder or bowel changes, or other red flags are present.

A stiff neck may respond to movement, exercise, mobilization, or selected manual therapy. Cervical thrust manipulation requires more careful risk assessment than simply locating a tight joint and applying force.
The physiotherapist reviews symptom onset, headache pattern, dizziness, visual or speech changes, neurological signs, trauma, medical history, and other features that may suggest a condition unsuitable for manipulation. The patient should understand the proposed technique, alternatives, expected benefit, and potential risks before consenting.
Many neck-pain patients can improve with lower-force mobilization, thoracic treatment, exercise, posture variation, strengthening, and activity modification without cervical thrust manipulation.

Sciatica describes symptoms related to irritation or involvement of a lumbar nerve root, commonly producing leg pain and sometimes numbness, tingling, or weakness. Not every pain traveling down the leg is sciatica, and not every case should be manipulated.
Manual therapy may help selected patients with back pain and sciatica when it is combined with exercise and appropriate advice. The physiotherapist must assess neurological function, symptom behavior, strength, reflexes, sensation, movement, and warning signs.
Progressive weakness, loss of bladder or bowel control, numbness around the saddle region, severe unrelenting pain, or rapid deterioration requires urgent medical assessment.
The phrase slipped disc is misleading because spinal discs do not simply slide out and wait to be pushed back. A disc may bulge, protrude, or irritate nearby structures, and many disc changes are also found in people without pain.
Manipulation cannot be promised to reverse an MRI finding or physically push a disc into place. Treatment should focus on the patient’s symptoms, neurological status, movement tolerance, function, and recovery over time. Exercise, education, gradual activity, and medical referral when necessary are often more important than repeated cracking.

There is no single perfect posture that every person must maintain. Posture changes throughout the day, and pain is influenced by movement variety, strength, workload, stress, sleep, and individual sensitivity.
Manual therapy may temporarily reduce stiffness, but it does not permanently hold the spine in a corrected position. Posture-related rehabilitation may include workstation changes, movement breaks, upper-back mobility, shoulder-blade control, trunk endurance, and gradual exposure to work or study demands.
Some headaches have a musculoskeletal component involving the neck, while others require medical or dental evaluation. Selected cervicogenic or tension-type headache presentations may improve with a combination of manual therapy, exercise, and education.
A sudden severe headache, new neurological symptom, fever, head injury, altered consciousness, visual disturbance, or unusual headache pattern requires medical assessment. Routine neck cracking should not be used to treat an undiagnosed headache.

Frozen shoulder primarily affects the shoulder joint and usually requires staged mobility, pain management, strength, and gradual restoration of function. Upper-back or neck stiffness may contribute to how the patient moves, but spinal adjustment is not a direct cure for frozen shoulder.
WHPT may treat connected spinal or shoulder-girdle impairments when they are clinically relevant, while keeping the rehabilitation focused on the shoulder itself.
Manipulation cannot straighten a structural scoliosis curve or permanently remove a spinal deformity. It may help selected symptoms such as stiffness or muscular discomfort, but expectations must remain realistic.
A visible upper-back curve, dowager’s hump, or posture change can have several causes, including structural shape, osteoporosis-related vertebral changes, muscle weakness, age-related changes, or habitual posture. Assessment is required before treatment, especially when fracture or osteoporosis is possible.
| Area | Chiropractor | Physiotherapist at WHPT Pakistan |
|---|---|---|
| Professional identity | A practitioner trained in chiropractic care where the profession is recognized and regulated | A physiotherapist trained in physical rehabilitation, movement, exercise, and manual therapy |
| Common focus | Musculoskeletal complaints, often using spinal manipulation and related conservative care | Pain, movement, strength, neurological and musculoskeletal rehabilitation, function, and return to activity |
| Spinal manipulation | Commonly used within chiropractic care | May be used by an appropriately trained physiotherapist when assessment supports it |
| Exercise rehabilitation | Varies by practitioner and model of care | Central to long-term recovery and progression |
| Provider at WHPT | WHPT does not represent its physiotherapists as chiropractors | Treatment is provided within a physiotherapy assessment and rehabilitation plan |
| Best choice | Depends on verified credentials, diagnosis, risks, goals, and quality of care | Appropriate when the patient needs assessment-led rehabilitation and active recovery |
The profession label alone does not guarantee quality. Patients should look for verified qualifications, informed consent, safety screening, realistic claims, reassessment, and a plan that promotes independence rather than indefinite dependence on adjustments.
Step 1: Clinical History
The physiotherapist reviews your pain, symptom behavior, medical history, trauma, medications, previous treatment, neurological symptoms, daily activities, and goals.
Step 2: Red-Flag and Safety Screening
The clinician considers fracture, infection, inflammatory disease, cancer, severe osteoporosis, neurological compromise, vascular concerns in neck presentations, and other reasons to avoid or modify manual therapy.
Step 3: Physical Examination
Movement, strength, sensation, reflexes where indicated, joint mobility, muscle function, balance, and relevant functional tasks are assessed.
Step 4: Explanation and Consent
The proposed treatment, expected sensation, possible benefits, limitations, alternatives, and risks are discussed. Consent can be withdrawn at any point.
Step 5: Manual Therapy
The physiotherapist may use mobilization, manipulation, soft-tissue treatment, or no hands-on treatment depending on the findings. Technique and force are individualized.
Step 6: Reassessment
Pain, range of motion, movement quality, or a relevant task is retested to determine whether the intervention produced meaningful change.
Step 7: Active Rehabilitation
Exercise, movement retraining, strengthening, mobility work, education, and a home program are used to build on any short-term improvement.
| Stage | What Happens | Why It Matters |
|---|---|---|
| History | Symptoms, medical conditions, trauma, medications, and goals are reviewed | Identifies possible risks and treatment priorities |
| Examination | Movement, neurology, strength, mobility, and function are assessed | Determines whether manipulation is relevant |
| Consent | Benefits, risks, alternatives, and patient preference are discussed | Supports an informed decision |
| Manual treatment | A selected technique is applied with appropriate force and positioning | Matches treatment to the patient rather than a routine |
| Reassessment | The intended outcome is retested | Shows whether the intervention added value |
| Rehabilitation | Exercise and self-management follow | Develops lasting capacity and independence |
When appropriately selected and combined with active care, potential benefits may include:
These are possible outcomes, not guarantees. Long-term recovery usually depends on the wider rehabilitation plan.
| Possible Benefit | What It May Allow | What It Does Not Automatically Do |
|---|---|---|
| Reduced pain | Easier movement and exercise | Diagnose or correct every cause of pain |
| Improved short-term mobility | Better tolerance of daily tasks | Permanently realign the spine |
| Reduced guarding | Progression into active treatment | Restore lost strength or endurance |
| Patient confidence | Less fear of movement | Prevent recurrence without behavior and capacity change |
| Immediate symptom change | Useful reassessment information | Prove that repeated manipulation is necessary |

Spinal manipulation is generally associated with temporary minor effects such as soreness, stiffness, fatigue, or a short-lived increase in symptoms. Serious complications are uncommon but possible, and risk differs by body region, patient health, technique, and underlying condition.
Cervical manipulation requires particular caution because neck pain or headache can occasionally be an early symptom of vascular or neurological disease. Screening cannot eliminate every risk, but a structured history, examination, clinical reasoning, informed consent, and willingness to choose a lower-force alternative are essential.
WHPT does not treat a loud crack as evidence of safety or success. The technique is avoided when the expected benefit does not justify the risk or when another approach is more appropriate.
Most people experience no serious problem after appropriately selected manual therapy, but temporary soreness, stiffness, fatigue, headache, or a short-lived increase in symptoms can occur.
WHPT screens risk before treatment and uses manual therapy only when the expected benefit justifies the technique.
Manipulation may be inappropriate, require modification, or require medical clearance when there is:
This list is not exhaustive. Contraindications depend on the region, technique, force, and individual medical circumstances.
Most people with uncomplicated nonspecific back or neck pain do not automatically need imaging before conservative treatment. Imaging may be appropriate when the history or examination suggests fracture, serious pathology, progressive neurological compromise, or another condition in which the result is likely to change management.
An X-ray should not be used merely to claim that the spine is “misaligned” or to justify a predetermined series of adjustments. WHPT recommends imaging or medical referral when clinically indicated.

There is no standard number. Some patients receive one trial of manual therapy and then progress mainly through exercise. Others may benefit from several sessions while their program develops. Treatment frequency depends on the condition, symptom duration, response, goals, risk profile, and active rehabilitation plan.
WHPT does not recommend indefinite maintenance cracking for every patient. Continued treatment should be justified by measurable improvement and a clear pathway toward self-management.
People often twist, pull, or use online techniques to create a popping sound. Repeated self-cracking may temporarily feel relieving, but the sound does not identify the source of symptoms or confirm that the chosen movement is safe.
Forceful self-manipulation of the neck is not recommended. A patient with persistent stiffness should be assessed and taught appropriate mobility, strengthening, and self-management strategies rather than chasing repeated pops.
Choosing a provider involves more than searching for the best chiropractor near you. The quality of assessment, verified professional training, safety screening, informed consent, honest expectations, and active rehabilitation matter more than the number of adjustments offered.
| WHPT Pakistan Approach | Why It Matters |
|---|---|
| Transparent professional identity | Patients know they are receiving physiotherapy-led manual therapy, not a falsely labeled chiropractic service |
| Assessment before manipulation | The technique is selected from clinical findings rather than requested automatically |
| Neurological and safety screening | Red flags and reasons to avoid or modify treatment are considered |
| Informed consent and alternatives | Patients understand benefits, uncertainty, risks, and lower-force options |
| Individualized force and technique | Mobilization, manipulation, exercise, or referral is chosen according to the patient |
| Reassessment after treatment | The clinician checks whether the intervention changed the intended outcome |
| Active rehabilitation | Strength, mobility, confidence, and function are developed beyond symptom relief |
| Same-gender care | Female patients receive female physiotherapists and male patients receive male physiotherapists |
| Referral when needed | Serious or unsuitable presentations are not hidden behind repeated adjustments |
A chiropractor commonly assesses and manages musculoskeletal complaints using spinal manipulation, exercise, education, and other conservative methods depending on training and practice style. WHPT provides physiotherapy-led spinal manual therapy rather than representing its clinicians as chiropractors.
In some countries, qualified chiropractors use the professional title Doctor of Chiropractic. They are not medical doctors unless separately medically qualified. Patients should verify the practitioner’s actual credential and regulatory status.
No. Chiropractic and physiotherapy are distinct professions, although both may treat musculoskeletal pain and some practitioners in each profession use manual therapy. WHPT clinicians are physiotherapists.
Spinal adjustment usually refers to manipulation. A popping sound may occur, but the clinical goal is a meaningful change in pain or movement, not the sound itself.
No. The common cracking sound does not prove that a vertebra was out of place or permanently realigned. Manipulation may influence pain and short-term movement without changing the basic position of the spine.
Manual therapy may help selected people with lower back pain, but assessment is more important than the professional label. Treatment should include advice and exercise rather than relying only on repeated adjustments.
It may help selected patients when combined with exercise and appropriate neurological assessment. Progressive weakness, bladder or bowel changes, or saddle numbness requires urgent medical care.
No clinician should promise to push a disc back into place. Disc-related symptoms are managed according to neurological findings, function, symptom behavior, exercise tolerance, and need for medical referral.
Many patients receive manual therapy without serious harm, but cervical manipulation has important risks and is not appropriate for everyone. A structured history, neurological and vascular consideration, informed consent, and alternatives are essential.
The technique may feel quick or unfamiliar, but it should not cause unnecessary sharp pain. Mild temporary soreness can occur. Tell the clinician immediately if you feel severe pain, dizziness, numbness, or another unusual symptom.
There is no fixed number. WHPT reviews treatment according to measurable progress and reduces passive care as the patient becomes able to manage through exercise and normal activity.
It may temporarily improve comfort or movement, but it does not permanently hold the body in a corrected position. Posture-related care usually requires movement variety, strength, ergonomics, and load management.
Selected cervicogenic or tension-type headaches may respond to a broader program including manual therapy and exercise. Sudden, severe, or unusual headaches require medical evaluation.
Yes. WHPT follows a same-gender care policy, subject to therapist availability and appointment scheduling.
The fee depends on whether the appointment involves an initial assessment, follow-up care, and the wider physiotherapy plan. Contact WHPT Pakistan on WhatsApp for the current consultation and treatment charges.
Manual therapy may help a patient move with less pain, but recovery often requires progressive strengthening, mobility, endurance, work conditioning, lifting practice, or a graded return to sport.
Where appropriate, WHPT patients can continue through clinic rehabilitation or transition to supervised long-term fitness at Alpha Fitness & Martial Arts Club. The aim is to reduce dependence on passive treatment and build the capacity needed for daily life.
WHPT assesses spinal pain, movement, neurological findings and relevant risks before selecting manual therapy, exercise or referral. Treatment is based on the person’s presentation rather than a promise to realign the spine.
Treatment selection should follow assessment, professional scope, patient preference and measurable response rather than habit or marketing claims.
The goal is clearer understanding, safer progression and greater independence.
If you are searching for a chiropractor in Lahore, a chiropractor near you, or spinal adjustment for back or neck pain, WHPT Pakistan offers a transparent physiotherapy-led alternative based on assessment, safety, and active rehabilitation.
We will help determine:
WHPT Resources

Understand upper back pain causes, common movement patterns, and warning signs that should not be ignored.
Read article →
Explore common causes of lower back pain, what symptoms may reveal, and when an assessment can help.
Read article →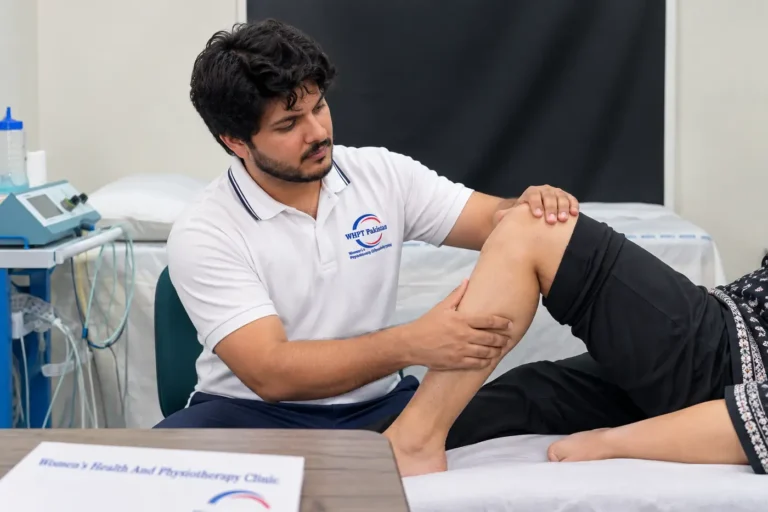
A knee assessment looks beyond pain alone. Learn how movement, strength, function, history, and symptoms guide rehabilitation.
Read article →
Some exercises may temporarily aggravate an irritated knee. Learn how to modify loading without giving up movement completely.
Read article →
Knee pain can return even after symptoms improve. Learn why recurrence happens and which factors may need more attention.
Read article →
Heat and ice can both help knee symptoms in certain situations. Learn when each option may be useful and what…
Read article →EXCELLENT Based on 19 reviews
 Posted on Google

 MUHAMMAD USMAN SALEEM MUHAMMAD SALEEMIt’s actually the place where Doctors have a right knowledge to treat. Strongly recommend best clinic in LahorePosted on Google
 Nasira ShaheenVery satisfied with the services and care given to my daughter from Dr. Rabail. She wasn't able to speak sentences and many words before and has improved more then that now in her behavior and speech. I am very grateful for Dr. Rabail and WHPT and had no concerns through our sessions with them.Posted on Google
 Mahnoor MughalMy father-in-law experienced severe low back spasms, and WHPT Pakistan's at-home physiotherapy service was a lifesaver. The therapist arrived fully equipped and provided highly effective, personalized care right in the comfort of our home. The treatment not only eased his pain but also gave him exercises to help prevent future episodes. The convenience and quality of care were superb, and we’re very grateful for their compassionate and professional service!Posted on Google
 Noaman Younasgood doctor team coprative doctorPosted on Google
 Ali AghadeerStaff is very professional and humble Great experiencePosted on Google
 Fatima ZahraI was tired of writing “physiotherapy near me” for my neck pain. Luckily, i ended up in WHPT Pakistan, arguably the most trusted physiotherapy clinic in Bahria Town Lahore. Highly recommendedVerified by TrustindexTrustindex verified badge is the Universal Symbol of Trust. Only the greatest companies can get the verified badge who has a review score above 4.5, based on customer reviews over the past 12 months. Read more
WHPT Pakistan
1st Floor, Plaza 82, Block AA Commercial,
Bahria Town, Lahore